




 TR
 EN
 DE
 Severe tooth loss and extensive alveolar bone resorption present complex challenges in modern oral rehabilitation, making the all on four treatment protocol one of the most reliable and clinically proven full-arch restoration methods available today. Living with multiple missing teeth or poorly fitting acrylic appliances significantly impairs masticatory function, alters facial proportions, and diminishes personal confidence. While conventional reconstructive techniques often require lengthy bone grafting procedures, prolonged healing periods, and substantial surgical intervention, the all on four approach overcomes these anatomic barriers through targeted biomechanical planning. By strategically inserting four precision-engineered titanium fixtures into key cortical areas of the jaw, clinicians establish robust primary stability capable of supporting a full arch of lifelike teeth. Two anterior fixtures stand vertically, while two posterior posts are tilted at deliberate angles up to 45 degrees, bypassing delicate structures such as the maxillary sinus cavities and the inferior alveolar nerve canal. Patients can walk out of surgery with a secure, aesthetic temporary bridge on the very same day, starting their journey toward lasting dental function and a rejuvenated smile.
What Is the All on Four Dental Treatment Concept?
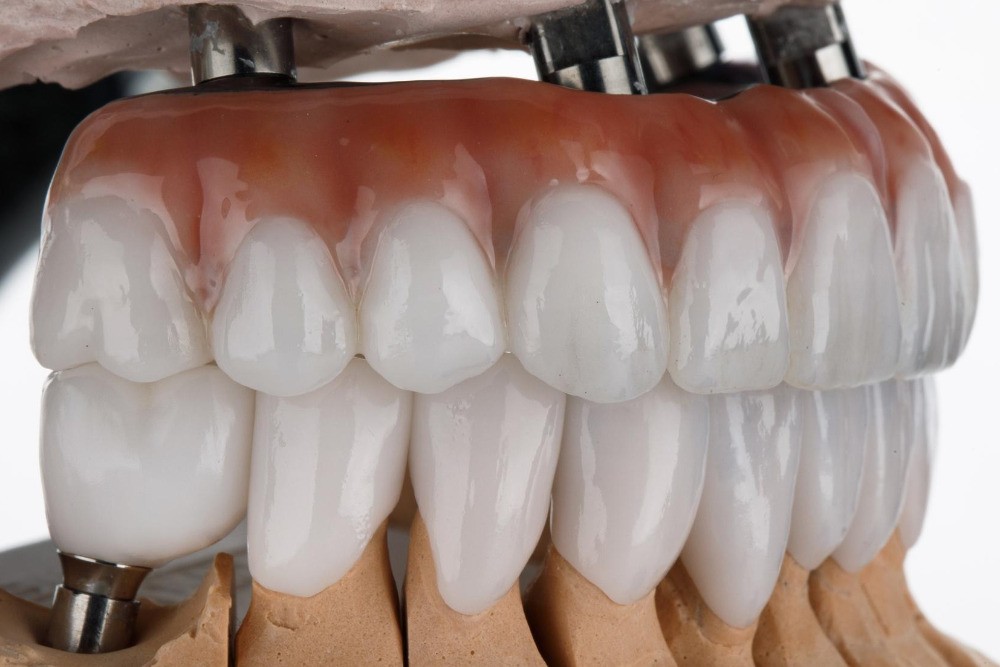
Pioneered in the late 1990s by European oral surgeons, this treatment concept is an immediate-load restorative methodology developed specifically to rehabilitate completely edentulous dental arches or jaws with failing terminal dentition. Rather than placing an individual fixture for every lost tooth, the protocol harnesses advanced principles of structural load distribution. The system relies on four strategically positioned dental implants to secure an entire rigid prosthetic arch consisting of ten to twelve replacement teeth.
The biomechanical foundation centers on tilting the two posterior fixtures. Angling these posts between 30 and 45 degrees increases bone-to-implant contact across denser cortical bone structures. Furthermore, tilting expands the prosthetic base anterior-posteriorly while minimizing posterior cantilevers. This structural arrangement allows clinicians to bypass anatomical boundaries, reduce surgical complexity, and deliver immediate functional restorations without the prolonged wait times common to historic grafting procedures.
How Does the Biomechanics of the All on Four System Work?
The success of full-arch reconstructions depends on rigid cross-arch stabilization and balanced distribution of occlusal forces. When masticatory pressure impacts an arch, force vectors travel through the prosthetic framework and distribute evenly across all four anchoring posts. By using rigid multi-unit abutments and a strong reinforced temporary bridge, micro-movements at the bone interface stay well beneath critical thresholds throughout the osseointegration window.
This cross-arch splinting protects the healing bone from destructive shear stress, encouraging steady osteoblast differentiation. By utilizing native bone in the anterior jaw—which tends to resorb much more slowly than posterior molar sites—the restoration maintains rigid stability even in compromised alveolar ridges. Patients can comfortably bite, speak, and smile without experiencing the shifting, clicking, or palate irritation common to removable acrylic appliances.
What Are the Clinical Advantages of the All on Four Protocol?
- Immediate Same-Day Function: Patients receive a stable, fixed temporary restoration within hours of surgery, completely avoiding toothless healing phases.
- Elimination of Invasive Bone Grafting: Tilted posterior placement takes advantage of available native bone, eliminating the need for sinus lifts and block grafts.
- Substantial Shortening of Overall Timelines: Bypassing multi-stage grafting and consolidation protocols cuts total rehabilitation time by several months.
- Preservation of Facial Structure: Deep osseous stimulation halts further alveolar bone resorption, preventing premature facial collapse and premature wrinkling around the lips.
- High Long-Term Clinical Predictability: Backed by over two decades of documented worldwide data, the approach consistently demonstrates success rates above 98%.
Who Is an Ideal Candidate for an All on Four Reconstruction?
This reconstructive technique is designed for individuals dealing with extensive oral degradation, advanced generalized periodontal attachment loss, widespread dental caries, or failing restorative crowns. It is equally suited for long-time denture wearers who struggle with loose lower plates, painful gum ulcerations, and reduced taste perception caused by full acrylic palatal coverage.
Candidates must exhibit sufficient bone density in the anterior jaw between the mental foramina in the mandible or between the maxillary sinuses in the upper jaw. Overall systemic wellness remains essential; conditions such as hypertension, well-managed diabetes, or history of controlled heart conditions are compatible with care once stabilized. In situations where localized single or dual tooth gaps exist amid strong native teeth, conventional dental implants remain the preferred conservative choice to preserve surrounding tooth structure.
Comprehensive Diagnostic Planning: 3D Scans and Surgical Guides
Cone Beam Computed Tomography (CBCT) Evaluation
Every case begins with ultra-low-dose high-resolution 3D radiographic mapping to analyze cortical bone density, assess ridge dimensions, and pinpoint nerve pathways and sinus floors with sub-millimeter precision.
Digital Photogrammetry and Intraoral Surface Scanning
Optical scanners map the soft tissue contours, current bite alignment, and smile dynamics, uploading digital data directly into specialized computer-aided implant planning platforms.
Static and Dynamic Computer-Guided Fabrication
Using digital software, surgeons determine the exact angle, depth, and rotational position of each implant fixture before 3D-printing precision surgical guides that streamline the surgical appointment.
How Does the Surgical Placement Procedure Work Step by Step?
The clinical appointment takes place under local anesthesia, conscious IV sedation, or general anesthesia, ensuring a relaxed, painless experience throughout. Any remaining non-restorable teeth are gently removed, followed by minor alveoloplasty to flatten the bony ridge, creating an even, hygienic foundation for the upcoming bridge.
Using custom 3D-printed guides, the surgeon prepares the osteotomy sites and inserts the four titanium fixtures. Multi-unit abutments are secured to the posts to balance angulations and bring restorative screw channels through non-aesthetic lingual surfaces. The clinical team then takes precise digital impressions, allowing the laboratory to mill and bond a reinforced, rigid temporary bridge onto the posts before the patient departs.
Immediate Loading: How Do Same-Day Teeth Function Safely?
Immediate provisionalization delivers transformative emotional and functional benefits, yet it requires strict adherence to biological principles. To load an implant right away, each fixture must reach an insertion torque of at least 35 to 45 Ncm, demonstrating solid mechanical lock in the bone. If bone quality is soft and cannot support that torque threshold, immediate loading is paused to ensure safe osseointegration.
When initial stability requirements are met, the temporary prosthesis acts as an orthopedic stabilization splint, connecting all four posts together so chewing forces spread across the whole arch. Throughout the initial three-month healing phase, patients stick to a soft diet, avoiding hard, crusty, or tough foods that could trigger micro-movements and interfere with the bone-healing process.
Comparing Full-Arch Fixed Implant Solutions
Selecting the optimal full-arch tooth replacement depends on bone availability, budget, treatment timelines, and structural considerations. The comparison below illustrates how this approach compares with removable alternatives and extended multi-post options:
| Restoration Criterion | All on Four Protocol | All on Six Protocol | Removable Dentures |
|---|---|---|---|
| Bone Volume Requirements | Minimal to moderate (Utilizes angulation) | Moderate to high (Requires back bone) | Minimal (Sits on top of mucosal gums) |
| Need for Bone Grafting | Rarely needed (Bypasses sinus & nerves) | Occasionally required in molars | None required |
| Fixation Type | Fixed, non-removable screw-retained | Fixed, non-removable screw-retained | Removable daily (Rests with suction) |
| Chewing Power Restored | Up to 90% – 95% of natural capability | Up to 95% – 100% of natural capability | Only 20% – 30% of baseline capability |
| Palatal Taste Interference | None (Horseshoe shape keeps palate open) | None (Open palate design) | High (Upper palate covered by acrylic) |
Evaluating the Differences Between All on Four and All on Six
Patients exploring full-arch rehabilitation often debate whether four or six implant posts provide the superior setup. While four posts easily handle full bites in patients with limited back bone height, moving to an All on Six treatment brings two extra posterior anchors into play. This setup shortens unsupported cantilever lengths and creates broader mechanical distribution across the dental arch.
Choosing six implants is particularly beneficial for younger patients, individuals with broader dental arches, or patients with strong jaw musculature who place higher mechanical stress on their restorations. The extra fixtures add mechanical redundancy, meaning the bridge remains stable even if a single post experiences issues years later. Your surgeon will evaluate your bone density and occlusal force patterns to determine the ideal setup for your anatomy.
Which Materials Are Used for the Final All on Four Prosthesis?
Monolithic Zirconia on a Titanium Substructure
Engineered from 100% biocompatible, non-porous ceramic blocks, monolithic zirconia resists chipping, prevents plaque adherence, and provides outstanding natural aesthetics alongside exceptional resistance against wear.
Titanium-Bar Reinforced High-Impact Composite
Combining a custom-milled internal Grade 5 titanium bar with nano-ceramic hybrid composite teeth, this setup cushions occlusal impact, making it well-suited for opposing natural teeth or mild clenching habits.
Metal-Acrylic Hybrid Bridges (The Classic Toronto Bridge)
Featuring a cast cobalt-chromium framework wrapped in pink gingival acrylic and composite denture teeth, this approach offers an accessible, easily repairable full-arch rehabilitation.
Why Do Patients Replace Removable Dentures with All on Four?
Removable plates have long served as an accessible option for addressing extensive tooth loss. However, their prolonged use accelerates alveolar bone resorption because forces press directly down onto delicate mucosal tissue. Patients often struggle with loose-fitting plates, shifting while talking, and relying on messy denture adhesives throughout the day.
While modern dentures in Turkey provide tailored aesthetics and comfortable fits for many individuals, fixed implant solutions deliver unmatched mechanical stability. Moving to an implant-supported bridge removes bulky palatal plastic entirely, restoring natural temperature sensation, clear speech, and full confidence when biting into apples, nuts, and meats without hesitation.
Cost Overview: All on Four Dental Pricing Around the World
Investing in comprehensive full-arch restorations involves evaluating significant price differences across international dental markets. Thanks to favorable exchange rates and lower operational laboratory expenses, Turkish clinics provide world-class European implants at considerable savings compared to Western fees. The pricing guide below outlines average full-arch restorative costs for 2026:
| Restoration Scope (Per Arch) | United Kingdom (£) | United States ($) | Turkey (€) |
|---|---|---|---|
| All-on-4 with Fixed Temporary Bridge | £7,500 – £11,000 | $12,000 – $18,000 | €1,800 – €2,400 |
| Final Monolithic Zirconia Bridge Upgrade | £3,500 – £5,500 | $5,500 – $9,000 | €1,200 – €1,600 |
| Complete Single Arch (Surgery + Final Zirconia) | £10,500 – £16,000 | $17,000 – $26,000 | €2,800 – €3,800 |
| Full Mouth All-on-4 (Upper & Lower Complete) | £20,000 – £30,000 | $32,000 – $50,000 | €5,400 – €7,200 |
| Intravenous (IV) Sedation Service | £600 – £1,000 | $1,000 – $1,800 | €250 – €400 |
How to Maintain Oral Hygiene Under an All on Four Bridge
- Use Specialized Floss Daily: Thread bridge floss or stiff-ended expanding floss under the pontic base to clean around abutment collars where plaque gathers.
- Incorporate Targeted Water Flossers: Direct an oral irrigator on a medium setting under the bridge to flush out trapped food debris and massage gum margins.
- Use Interdental Brushes: Gently run soft, plastic-coated interdental brushes between the bridge underside and gum line to remove lingering biofilm.
- Choose Low-Abrasive Pastes: Clean with non-abrasive fluoride toothpastes to keep your prosthetic surfaces and titanium components smooth and scratch-free.
- Schedule Professional Cleanings: Visit your hygienist every six months for ultrasonic scalers equipped with carbon-fiber tips that clean safely without scratching titanium surfaces.
How Long Does an All on Four Restoration Last in Clinical Practice?

Clinical studies following patients over 15 to 20 years show exceptional outcomes, with implant fixture survival rates consistently hovering between 95% and 98%. The titanium posts integrate with jawbone biology and can last a lifetime when supported by healthy habits and diligent oral hygiene.
While the integrated posts are permanent, the prosthetic bridge itself naturally undergoes mechanical wear over decades of daily chewing. Acrylic components typically require servicing, polishing, or tooth replacement after 7 to 10 years, whereas monolithic zirconia designs can easily last 15 to 20 years or longer. Managing nocturnal teeth clenching with a custom nightguard protects both the framework and bone interface from unnecessary mechanical stress.
What Are the Common Risks and Post-Surgical Complications?
Early Loss of Biological Osseointegration
If an implant fails to integrate due to unexpected infection or premature bite loading, it can be gently replaced with an adjusted diameter fixture after a brief healing window.
Peri-Implantitis and Marginal Bone Loss
Similar to periodontitis around natural roots, plaque accumulation can trigger chronic gum inflammation and bone loss, highlighting the importance of thorough home hygiene routines.
Mechanical Prosthetic Complications
Heavy chewing forces or nocturnal clenching can sometimes loosen bridge screws or cause minor cosmetic chipping, issues that can usually be resolved in clinic without disturbing the integrated posts beneath.
Why Choose Klinik 29 in Istanbul for Your All on Four Treatment?
Located in the heart of Istanbul, Klinik 29 provides advanced surgical care and restorative artistry for patients traveling from across the globe. Our experienced maxillofacial surgeons and prosthodontists utilize advanced low-radiation CBCT imaging, computer-guided implant planning, and dynamic placement systems to insert every fixture with sub-millimeter precision.
We work exclusively with certified, lifetime-warranted implant brands and maintain an on-site digital CAD/CAM milling laboratory to ensure every prosthesis fits comfortably and looks entirely natural. Backed by transparent pricing, dedicated patient coordinators, and attentive post-operative follow-up, Klinik 29 delivers dependable full-arch care that restores stable chewing function, facial balance, and lasting smile confidence.

Dr. Kıvanç Türkoğlu

Dr. Pınar Türkoğlu

Dr. Başak Topuzoğlu

Dr. Lebriz Yalçın Gürhan

Dr. Sinem Kösem Mihmar

Dr. Dt. Gürcan Çetin




